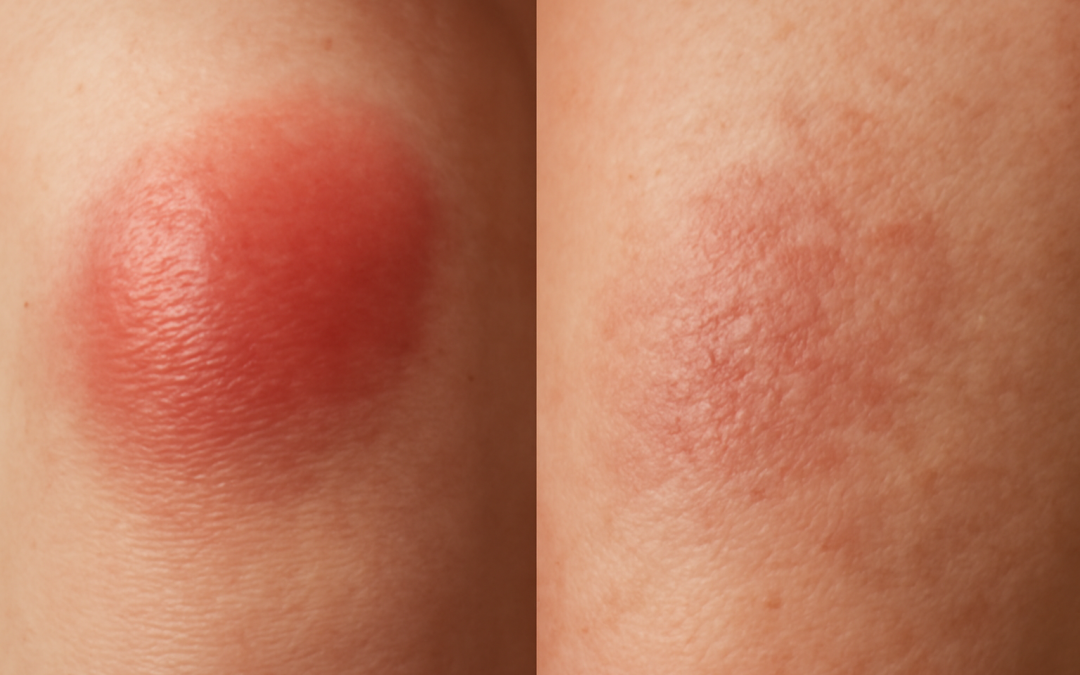
Inflammation is a natural and essential part of the body’s immune response, acting as both a defense mechanism and a healing process. When the body encounters injury, infection, or harmful stimuli, it initiates a complex biological reaction to protect and repair the affected tissues. However, not all inflammation is the same. Understanding the differences between acute and chronic inflammation is crucial for recognizing how the body responds to various threats and why some conditions can become long-lasting and detrimental. This discussion delves into the defining characteristics, underlying causes, biological processes, and health implications of acute and chronic inflammation.
Acute inflammation is the body’s immediate and short-term response to an injury or infection. It begins quickly and generally resolves within a few days or weeks. The primary goal of acute inflammation is to contain and eliminate the injurious agent, clear away damaged cells, and initiate tissue repair. Common triggers include microbial infections, physical trauma, chemical irritants, or immune reactions. When injury occurs, blood flow to the affected area increases as blood vessels dilate, allowing immune cells like neutrophils to migrate rapidly to the site. These cells work to engulf and destroy pathogens or debris, producing signaling molecules such as cytokines and chemokines that recruit additional immune cells.
The clinical signs of acute inflammation—redness, heat, swelling, pain, and loss of function—are easily recognizable and result from the underlying physiological processes. Vasodilation causes redness and heat by increasing blood flow, while increased vascular permeability allows plasma proteins and leukocytes to exit the blood vessels and infiltrate the injured tissue, causing swelling. Pain arises due to the stimulation of nerve endings by inflammatory mediators like prostaglandins. This response is finely tuned to provide maximum protection with minimal tissue damage and typically subsides once the threat is neutralized and repair begins.
In contrast, chronic inflammation is a prolonged inflammatory response that can last for months or even years. It occurs when the initial acute response fails to eliminate the cause of inflammation or when low-grade, persistent factors continually stimulate the immune system. This type of inflammation is often invisible without medical testing because it lacks the classical acute symptoms. Chronic inflammation is implicated in numerous diseases including autoimmune disorders, cardiovascular disease, diabetes, and certain cancers. It involves a different set of immune cells, primarily macrophages, lymphocytes, and plasma cells, which contribute to ongoing tissue damage and attempts at repair.
Unlike acute inflammation, which focuses on rapid resolution, chronic inflammation represents a maladaptive process where the inflammatory response becomes dysregulated. The persistent production of inflammatory mediators can lead to fibrosis, tissue destruction, and altered cellular function. In the case of autoimmune diseases, for example, the immune system mistakenly targets normal tissues, resulting in continuous inflammation. Similarly, chronic exposure to irritants such as tobacco smoke or industrial pollutants can maintain a state of low-level inflammation that damages tissues over time.
The cellular and molecular mechanisms underlying acute and chronic inflammation are distinct but interconnected. Acute inflammation is largely driven by innate immune cells that recognize pathogens or damaged cells through pattern recognition receptors. This triggers a cascade of events involving the complement system, cytokine release, and recruitment of neutrophils. These neutrophils not only attack invaders but also release enzymes that break down damaged tissue, facilitating the repair process. Once the acute phase subsides, macrophages help to clear apoptotic neutrophils and orchestrate tissue healing.
In chronic inflammation, the adaptive immune system becomes increasingly involved. This phase is characterized by infiltration of T cells and B cells, which sustain the inflammatory response by producing cytokines and antibodies. Macrophages switch to a more activated phenotype that perpetuates inflammation and tissue damage. Moreover, fibroblasts are activated, leading to excessive extracellular matrix deposition and fibrosis. The disruption of normal tissue architecture in chronic inflammation contributes to the development of scar tissue and impaired organ function.
The triggers for acute and chronic inflammation can sometimes overlap but generally differ in nature and duration. Acute inflammation results from an identifiable and usually transient injury or infection, such as a cut, bacterial infection, or allergic reaction. Since it is a protective response, acute inflammation can be seen as beneficial and necessary for survival. Treatment often involves rest, ice, compression, elevation (RICE), and anti-inflammatory medications that limit excessive tissue damage while allowing healing to proceed.
Chronic inflammation, on the other hand, usually stems from persistent infections, autoimmune disorders, prolonged exposure to irritants, or systemic metabolic disturbances such as obesity. In these cases, the inflammatory process does not resolve, and the ongoing presence of inflammatory cells can lead to a vicious cycle of tissue injury and repair. Managing chronic inflammation often requires addressing the underlying cause, such as controlling blood sugar in diabetes, using immunosuppressive drugs for autoimmune diseases, or lifestyle changes to reduce exposure to toxins.
Biomarkers and diagnostic tools are vital for distinguishing between acute and chronic inflammation. In clinical settings, acute inflammation often correlates with elevated white blood cell counts, increased levels of C-reactive protein (CRP), and other acute-phase reactants detectable in blood tests. Chronic inflammation may not exhibit such dramatic changes but can be identified through prolonged elevations of inflammatory markers like erythrocyte sedimentation rate (ESR), tumor necrosis factor-alpha (TNF-α), or interleukin-6 (IL-6). Imaging technologies can also reveal structural changes in tissues caused by chronic inflammatory processes.
The impact of chronic inflammation on overall health cannot be overstated. Research increasingly shows that persistent inflammation plays a central role in the progression of many degenerative diseases. For example, in atherosclerosis, chronic inflammation in the blood vessel walls leads to plaque buildup and increased risk of heart attack and stroke. In neurodegenerative diseases like Alzheimer’s, inflammatory processes contribute to neuronal death and cognitive decline. Managing inflammation is thus a critical component of preventive medicine and therapeutic strategies.
Diet and lifestyle choices have significant effects on the regulation of inflammation. Diets high in processed foods, sugar, and unhealthy fats are linked to elevated chronic inflammation, whereas diets rich in fruits, vegetables, whole grains, and omega-3 fatty acids can help modulate immune responses and reduce inflammatory markers. Regular exercise also appears to have anti-inflammatory effects, partly by reducing visceral fat and altering cytokine profiles. Avoiding smoking, managing stress, and getting adequate sleep are additional measures that help maintain balanced immune function.
Pharmacological interventions vary depending on whether inflammation is acute or chronic. Nonsteroidal anti-inflammatory drugs (NSAIDs) and corticosteroids are commonly used to reduce symptoms during acute inflammatory episodes. While effective in short-term use, these drugs can cause unwanted side effects, especially when used long-term. For chronic inflammatory conditions, disease-modifying antirheumatic drugs (DMARDs) and biologic agents targeting specific inflammatory pathways offer more precise treatment options. These have revolutionized the management of autoimmune diseases but require careful monitoring.
Future research continues to explore novel targets for controlling inflammation more effectively and safely. Understanding the molecular triggers that switch acute inflammation into chronic pathology offers hope for new therapeutic strategies. Advances in personalized medicine, including genetic profiling and microbiome analysis, are reshaping how chronic inflammatory diseases are diagnosed and treated. Additionally, there is growing interest in natural compounds and lifestyle interventions that can influence inflammation without the risks associated with conventional drug therapies.
Educating individuals about the signs and risks of chronic inflammation is crucial for early intervention and prevention of associated diseases. While acute inflammation signals an immediate problem that often resolves with appropriate care, chronic inflammation tends to be silent and insidious, contributing to systemic damage over time. Awareness of personal risk factors, regular health check-ups, and adherence to recommended treatments can greatly reduce the burden of chronic inflammatory conditions.
Both acute and chronic inflammation are complex biological processes with distinct roles in health and disease. Acute inflammation is vital for protecting the body and initiating repair, while chronic inflammation, when unchecked, can contribute to the development and progression of numerous pathological conditions. Recognizing the differences between these two types of inflammation enhances clinical diagnosis, guides appropriate treatment, and informs preventive health measures. Ultimately, maintaining balanced inflammatory responses is key to promoting long-term health and resilience against disease.